Cancer Society, in Shift, Has Concerns on Screenings
Thursday, October 22, 2009
Cancer screening
Finally... For those who haven't yet read this article in the NY Times, worthwhile reading.
Cancer Society, in Shift, Has Concerns on Screenings
Cancer Society, in Shift, Has Concerns on Screenings


Sunday, April 19, 2009
Guest entry: Domestic violence and narcissist personality disorder
posted by Antigone Kostas, MD (psychiatry resident)
The cycle of violence in domestic abuse: The abusive husband hits his wife and, while the wife may then leave, after many pleas from the husband that he’ll never do it again and that he truly loves her, she’s back with him, for a period of relative peacefulness (the honeymoon phase) - only to be hit again and for the cycle to repeat.
Why does the wife go back to the abusing husband? And who is the abusing husband? In his paper, “Dyadic Violence, Shame, and Narcissism,” Stewart Hockenberry, a psychologist, explores who these people may be and why this happens. He claims that in many situations it is the play between two different narcissistic characters—the Grandiose Narcissist and the Symbiotic Narcissist.
A narcissist is often a person "who is full of him/herself." Narcissists have grandiose views of themselves, often to oddly enough buoy themselves against feelings of low self-esteem. Characteristics of narcissists include using other people for their own gains and lacking empathy.
So, first, how does a narcissist develop? Hockenberry finds that, “Early childhoods are variously characterized by narcissistic injuries linked to abandonment, separation, lack of parent-child attunement, neglect, impingement, and abuse; each shares a unifying theme of profound, inescapable, and self-negating shame.” Thus the narcissist is very much the shamed, wounded child.
The grandiose narcissist hides his shame and feelings of inadequacy by “playing the big man.” Moreover, the grandiose narcissist, because of his shame and self-hatred, finds someone else upon whom he can “project his own frustration and thus dissociate from these feelings of self-hatred. By projecting these feelings onto someone else, the grandiose narcissist can triumph over his internal shame by ‘revenge.’”
In an abusive relationship this plays out usually after the honeymoon phase. During the honeymoon phase, the other person is “loved and idealized as long as domination and complete control of their responses can be assured.” However, when things do not go according to plan, the narcissist feels attacked and strikes back.
The example Hockenberry gives is that of a doting man on a woman who soaks up all the adoration and makes no complaints. As the story goes, this cannot go on forever and when the woman starts to point out needs of her own or to have a few complaints, the grandiose narcissist goes into a narcissistic rage—feeling attacked-- and is ballistic.
But who pairs up with the grandiose narcissist? Hockenberry counters that it is often a narcissist as well - a symbiotic narcissist. The symbiotic narcissist also has shame, but is instead self-deprecating, turning her anger/aggression inward and living by martyrdom. She often feels responsible for other people’s pain and anger - suffering becomes familiar and even natural.
The symbiotic narcissist was “raised in control-oriented, oppressive environments, in which at least one of the parents was intrusive or invasive of personal boundaries, [and] the individual attachments are tenuously maintained, often at the cost of considerable pain and suffering. Because of overwhelming needs for attachment and bonding, actual abuse and suffering are frequently denied or are seen in themselves as signs of attachment.”
So the grandiose narcissist seeks out those he can degrade when the situation feels out of hand, while the symbiotic narcissist eats up the suffering. Hence the cycle of attack/revenge and victimization/suffering continues.
Bibliography
Hockenberry, Stewart L., “Dyadic Violance, Shame, and Narcissism,” Contemporary Psychoanalysis, Vol 31, No.2 (1995).
Monday, March 16, 2009
Alzheimer's, dysphagia, and PEG tubes – a conversation
Grandpa had been gradually declining from Alzheimer's dementia for years (he was confined to bed and he could no longer communicate with his family), but on this visit, after he was admitted to the hospital with pneumonia for the second time in a few months, it was clear he was now also having difficulty swallowing (dysphagia in medical terms). Grandpa was choking on the simplest of foods, including liquids and pureed foods, when he was tested by the speech therapist. Even when slowly fed small spoonfuls he wasn't safe to eat.
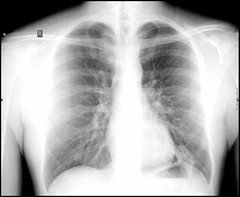
(image of pneumonia by Tim Snell, http://www.flickr.com/photos/timsnell/2347749472/)
“How will he get food?” the family asked.
“We have a couple of options,” the doctor began. “One is to entirely bypass his mouth and throat, where all the difficulty is, by placing a tube, a PEG tube through the skin of his abdomen directly into his stomach. The tube can then be used to feed him, give him medicines, etc.”
“Is that major surgery?” the family asked.
“Although not without risks, it's a relatively simple procedure. The gastroenterologists place PEG tubes relatively often and serious complications are rare. The procedure is performed by passing a camera through the mouth down into the stomach, in the same way that upper endoscopies (EGDs) to view the esophagus and stomach are performed. There the gastroenterologists shine a light up at the skin and where that light is seen on the skin is where they place the tube.”
“Sounds worth doing,” the family said.
“From what I've told you so far I'd have to agree, except as usual nothing is quite so straightforward. For instance, there is some controversy as to how effective the PEG tube truly is in patients like Grandpa, whether the tube truly prevents aspiration (food going into the lungs) any more than merely trying to carefully feed him by mouth slowly and with small spoonfuls.
Despite all of us having a sphincter or valve at the lower part of our esophagus to keep stomach contents from coming back up, we all at some point during the day, usually at night, likely allow some stomach contents into our lungs. We aspirate. Similarly, even with the PEG tube some of the contents from Grandpa's stomach will find their way into his lungs. The difference between us and Grandpa, though, is that we are able to protect our lungs. If food or stomach contents go the wrong way, we quickly cough them up. Grandpa can't as I'm sure you've noticed by his really weak cough.”
“So if we don't place a PEG tube?” the family asked.
“The other option is to merely let Grandpa eat and accept the fact that some food will likely go the wrong way and into his lungs with all the risks that entails, including more pneumonias and potentially death.1
Sounds terrible, I know, but where we are now with Grandpa, with dysphagia and food going into his lungs, is part of the natural progression of Alzheimer's. It is common and generally signifies that the Alzheimer's patient is severely impaired and that life expectancy is short. And the benefit of placing a PEG tube in a terminally ill patient, sadly, is unclear.
Knowing that, not everyone would want an artificial feeding tube.2 In fact, letting Grandpa eat and take those risks is a reasonable option, and one that many families choose.3
The question in the end is what would Grandpa have wanted? If Grandpa were able to be here today and tell us, what would he say?
“I have a question,” one family member asked, “If we place the tube, can he still eat?”
“While he can still eat with the PEG tube, the main reason for us to place the tube, would be to try to minimize his risks. It would make less sense in Grandpa's case to both place the tube and let him eat.
If we do choose to allow Grandpa to eat, however, knowing that Grandpa will continue to develop pneumonias, I would suggest that the next time he does that we don't actually transfer him back to the hospital. Rather than us at the hospital trying to help him recover from that pneumonia in order to be healthy enough to go through the process all over again, I would leave these issues to his regular doctor to manage and, if necessary, to make Grandpa comfortable. It is another difficult decision but one worth considering...
Another way to think about these issues is what do we really want to accomplish? PEG tubes, for instance, make for easier delivery of medications, but if we are trying to have Grandpa live longer or have a better quality of life, that may be unrealistic.”4
2You would think that swallowing is as hardwired as anything else in our body, like a reflex or our heart beating, something that requires no thought and would never go, but that isn't true. It actually requires a level of brain function to effectively coordinate all the movements of swallowing: to chew, push food to the back of the pharynx, initiate the swallow, etc.
3Nutrition is seen as a symbol of life and withholding full nutrition, in some way letting a family member go, letting them pass, even if naturally, can be difficult for families; yet, in many ways this dilemma developed only as a result of modern technology, our ability to place feeding tubes, give antibiotics, etc.
4An unintended consequence which people don't usually consider is that every time Grandpa returns to the hospital and is treated for pneumonia with antibiotics, the risk of creating more and more drug resistant bacteria increases. The fear from a medical and societal perspective is the development of bacteria potentially resistant to all known antibiotics.
Subscribe to:
Posts (Atom)


 Posts

